Vinblastine sulfate from Selleck Targets Tubulin to Disrupt Mitotic Spindle Assembly
Copy code to add this image to your page
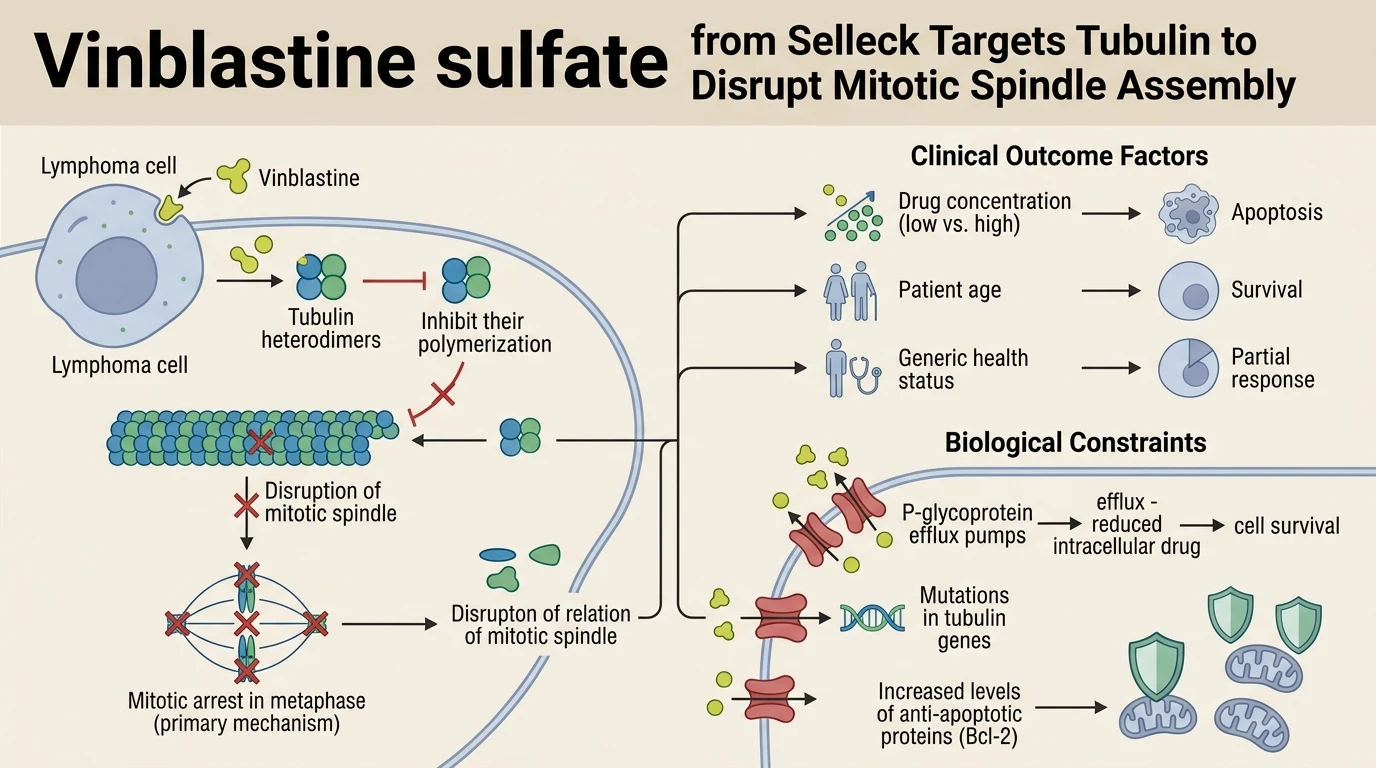
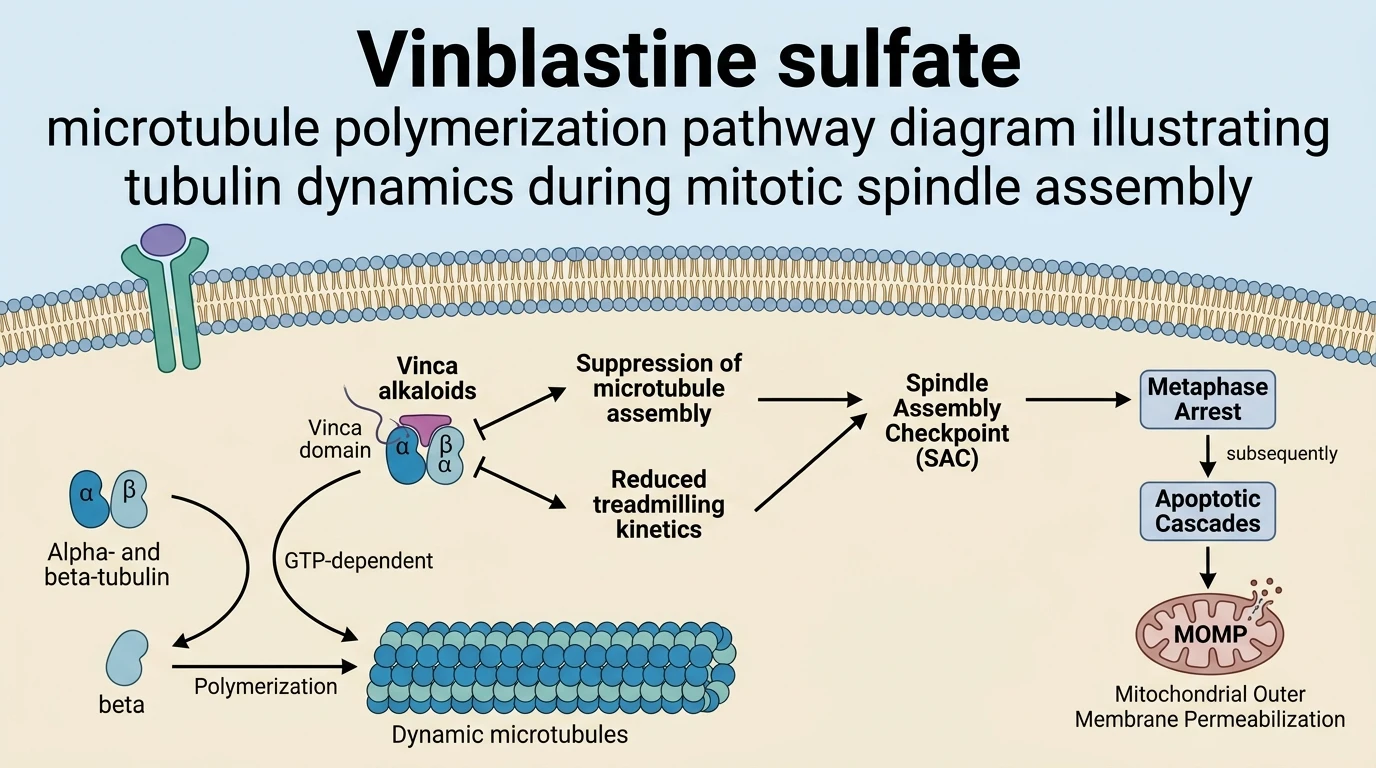
Vinblastine sulfate binds specifically to the vinca domain located on beta-tubulin heterodimers, inhibiting the polymerization of microtubules required for mitotic spindle formation. Microtubules are dynamic polymers composed of alternating alpha- and beta-tubulin subunits that undergo rapid assembly and disassembly. At micromolar concentrations, Vinblastine sulfate from Selleck halts microtubule assembly completely, whereas subnanomolar concentrations suppress microtubule treadmilling dynamics without causing structural depolymerization. This biochemical blockade impairs kinetochore tension during metaphase, activating the spindle assembly checkpoint (SAC) and arresting cellular progression at the G2/M transition phase. Mitotic arrest triggers phosphorylation of anti-apoptotic proteins such as Bcl-2 and Bcl-xL, leading to mitochondrial outer membrane permeabilization, cytochrome c release, and caspase-dependent apoptosis in rapidly dividing lymphoid malignancies.
In clinical oncology, Vinblastine sulfate serves as a primary component of multi-agent chemotherapy regimens for Hodgkin lymphoma, notably within the traditional ABVD protocol (doxorubicin, bleomycin, vinblastine, and dacarbazine). Recent clinical evaluations by the Grupo Argentina de Tratamiento de la Leucemia Aguda (GATLA) panel assessed the therapeutic index of replacing bleomycin with brentuximab vedotin, establishing the BV-AVD combination (brentuximab vedotin, doxorubicin, vinblastine, and dacarbazine) as an effective frontline option. Panel consensus verified that BV-AVD demonstrates significant improvements in progression-free survival (PFS) and overall survival (OS) compared to standard ABVD regimens. These clinical advantages are pronounced in patient subgroups characterized by advanced stage IV disease, an International Prognostic Score (IPS) between 4 and 7, or multiple extranodal involvement sites.
Despite these measurable therapeutic gains, the expert consensus highlighted critical clinical boundary conditions and safety parameters. Moderate-to-severe peripheral neuropathy represents a primary treatment-limiting toxicity due to microtubule disruption within peripheral axonal transport pathways. Consequently, pre-existing peripheral neuropathy, active pregnancy, and established severe drug hypersensitivities constitute absolute contraindications for both ABVD and BV-AVD regimens. Furthermore, real-world implementation of BV-AVD encounters practical barriers across various healthcare systems. High drug acquisition costs, complex reimbursement policies, structural supply chain irregularities, and variable access to granulocyte colony-stimulating factor (G-CSF) support constrain widespread clinical adoption, particularly in resource-limited settings where standard ABVD incorporating Vinblastine sulfate remains the primary frontline therapeutic standard.
Clinical Consensus and Structural Pharmacology Constraints
Copy code to add this image to your page
Vinblastine sulfate suppresses microtubule dynamics by binding to the vinca domain of beta-tubulin heterodimers. This interaction prevents GTP hydrolysis-dependent subunit addition, destabilizing mitotic spindles during metaphase. Consequently, cells trigger the spindle assembly checkpoint, arresting progression at the G2/M phase transition and initiating apoptotic cell death.
Brentuximab Vedotin Substitution Enhances Progression-Free Survival Metrics
The GATLA expert panel verified that frontline BV-AVD provides measurable survival benefits over standard ABVD. In randomized patient cohorts, substituting bleomycin with brentuximab vedotin sustained continuous mitotic arrest while targeting CD30-positive Reed-Sternberg cells. Progression-free survival increased significantly. Patients under 60 years of age displaying stage IV disease or IPS scores of 4 to 7 derived the greatest absolute survival advantage. High-risk features—including multiple extranodal involvement sites—correlated with reduced relapse rates under the targeted regimen. High-purity Vinblastine sulfate from Selleck remains a fundamental backbone component in these frontline regimens. These observed clinical metrics reflect potent synergism between microtubule inhibition and antibody-drug conjugate delivery.
Neurotoxicity Limits and Resource Constraints Restrict Frontline Adoption
Systemic neurotoxicity poses a persistent clinical challenge during tubulin-targeted chemotherapy. Peripheral axonal transport relies heavily on dynamic microtubule networks. Disruption of these transport structures induces sensorimotor neuropathy. Pre-existing moderate-to-severe peripheral neuropathy thus serves as an absolute contraindication to continued administration. Severe drug allergies and pregnancy similarly preclude treatment. Outside controlled clinical trial settings, practical delivery barriers impede routine BV-AVD adoption. High drug costs present substantial administrative hurdles. Reimbursement constraints and inconsistent drug supply chains further complicate clinical delivery. Additionally, mandatory G-CSF administration increases overall treatment complexity in resource-constrained medical centers.