Ceritinib (LDK378) Inhibits ALK Tyrosine Kinase to Induce Complete Pathological Response in NSCLC
Copy code to add this image to your page
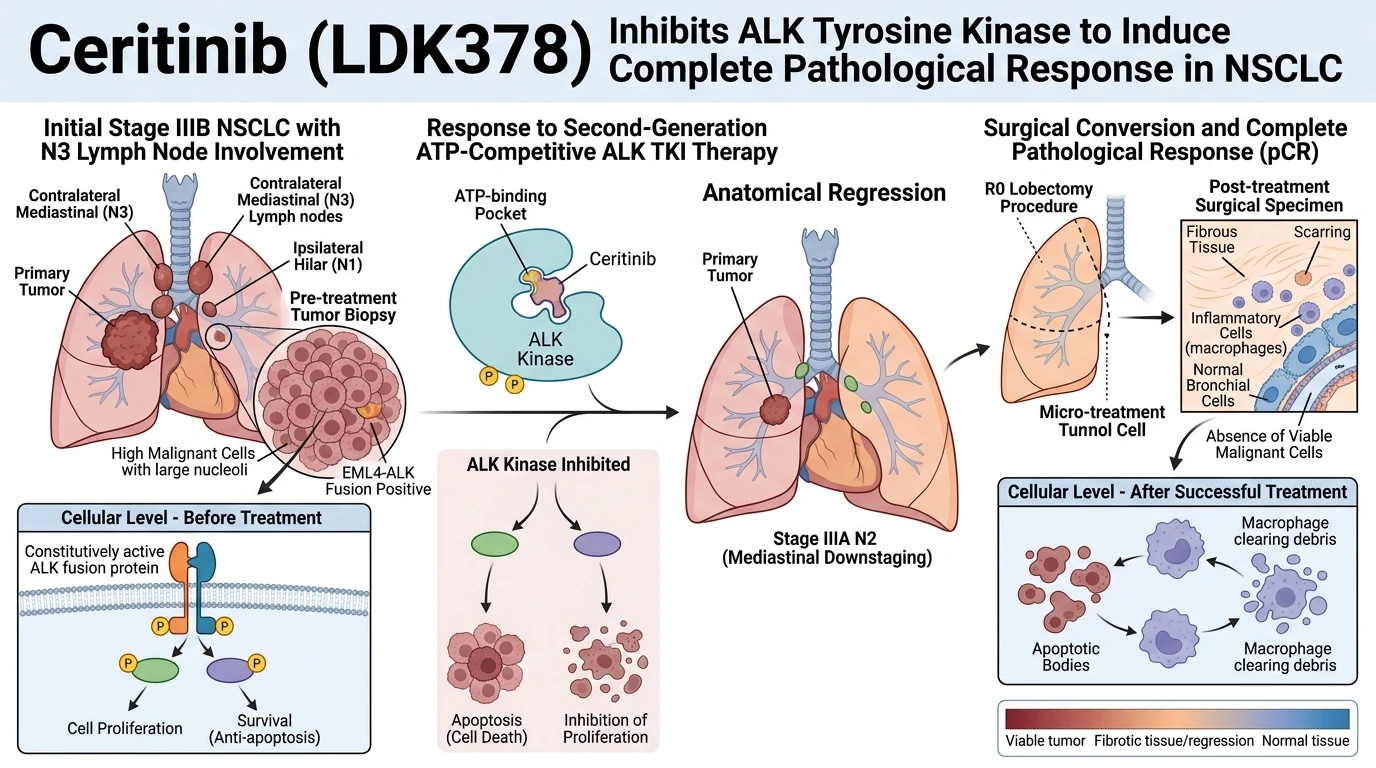
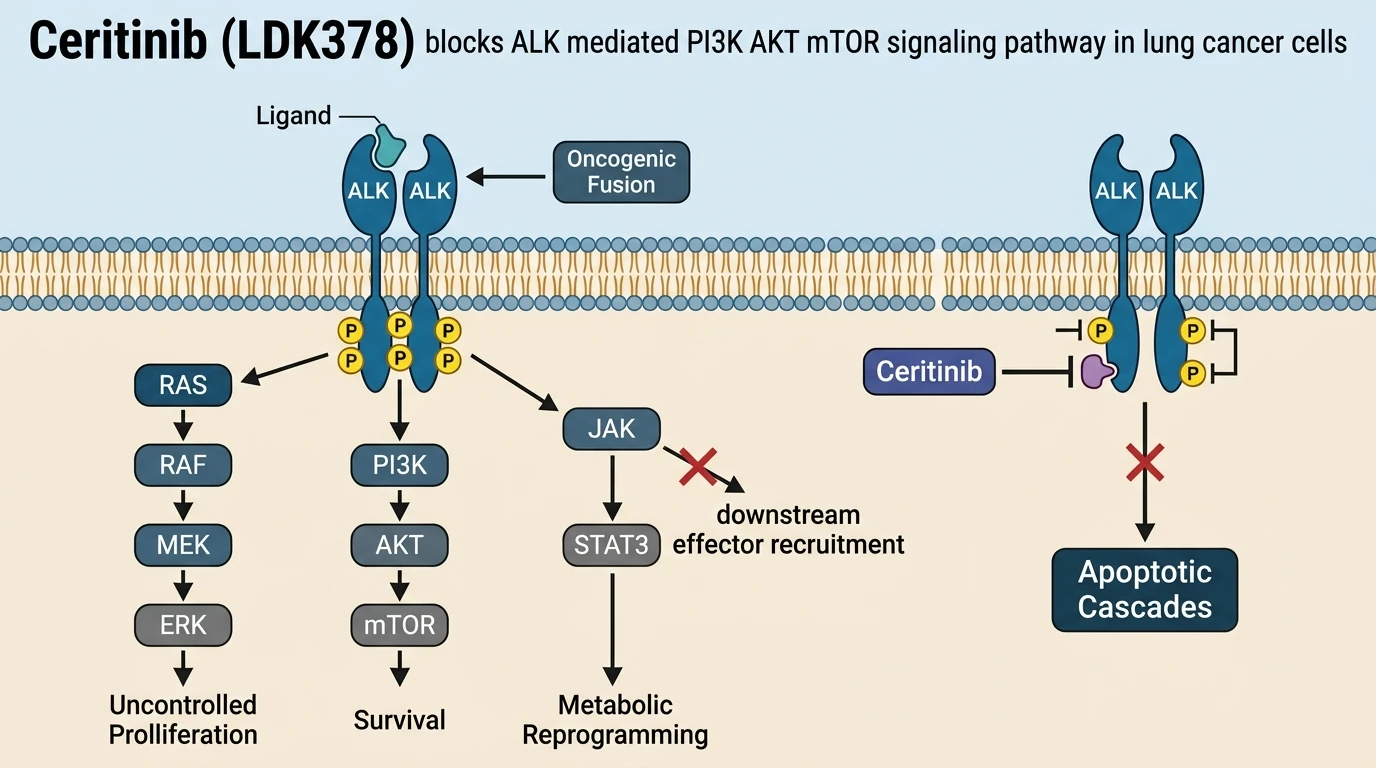
The oncogenic activation of Anaplastic Lymphoma Kinase (ALK) arising from chromosomal rearrangements—most frequently yielding the EML4-ALK chimeric fusion gene—drives aberrant signaling through constitutive kinase activation. While first-generation inhibitors like crizotinib initially achieve clinical responses, resistance inevitably emerges through secondary kinase domain mutations, activation of bypass signaling pathways, or inadequate drug exposure in sanctuary sites. Ceritinib (LDK378) is a second-generation, oral, small-molecule ATP-competitive ALK inhibitor engineered specifically to overcome crizotinib resistance mechanisms. Structurally built around a 2,4-diarylaminopyrimidine scaffold, Ceritinib (LDK378) demonstrates a 20-fold greater potency against ALK tyrosine kinase activity in cell-free enzymatic assays relative to crizotinib, effectively suppressing both wild-type ALK and mutant variants such as L1196M, C1156Y, I1171T, and G1269A under tested in vitro conditions. In structural docking studies, Ceritinib (LDK378) forms crucial hydrogen bonds within the hinge region of the ALK kinase domain, specifically interacting with the backbone amino acid residue Met1199. The 2-isopropoxy-5-methylphenyl group projects into a hydrophobic pocket created by the kinase domain conformation, providing steric clearance that accommodates mutations at the gatekeeper residue L1196. Furthermore, the piperidine ring moiety extends toward the solvent-exposed region, optimizing pharmacokinetic properties including tissue distribution and brain-to-plasma concentration ratios. The primary mechanism of action involves competitive binding to the ATP catalytic binding site of the ALK intracellular domain, which blocks autophosphorylation at key tyrosine residues, specifically Y1278, Y1282, and Y1283. Prevention of receptor transphosphorylation arrests downstream signaling cascades, including the RAS/RAF/MEK/ERK, PI3K/AKT/mTOR, and JAK/STAT3 pathways. Inhibition of these cascades suppresses transcription of anti-apoptotic proteins such as BCL-2 and BCL-XL, inducing caspase-dependent apoptosis and cellular G1-phase cell cycle arrest in ALK-dependent cellular models. While second-generation ALK tyrosine kinase inhibitors are established standard-of-care agents in advanced metastatic NSCLC, their application in the neoadjuvant setting for locally advanced, unresectable disease represents an emerging therapeutic strategy. A documented clinical case illustrates this strategy in a patient with stage IIIB(N3) NSCLC harboring an ALK rearrangement who exhibited disease progression on first-line crizotinib. The presence of biopsy-proven contralateral mediastinal lymph node involvement (N3 disease) initially categorized the patient as inoperable under standard thoracic oncology guidelines. Following therapy transition, neoadjuvant Ceritinib (LDK378) administration prompted dramatic metabolic and anatomical regression. Longitudinal 18F-FDG PET-CT imaging revealed marked clearance of radiotracer avidity within the primary lung tumor and contralateral lymph node stations. This profound therapeutic response downstaged the disease from stage IIIB(N3) to stage IIIA(N2), successfully clearing contralateral nodal disease and rendering the primary lesion surgically accessible. Surgical intervention comprised a right lower lobe lobectomy accompanied by systematic mediastinal lymph node dissection. Pathological evaluation of the resected parenchymal and nodal tissues confirmed an R0 surgical resection margin. Microscopic assessment revealed complete loss of tumor viability, characterized by extensive fibrotic scarring, histiocytic aggregates, and necrotic debris without residual malignant epithelial cells, establishing a pathological complete response (pCR). At 12 months post-surgery, the patient remained free of disease recurrence without adjuvant treatment. These clinical observations illustrate that neoadjuvant Ceritinib (LDK378) can induce significant pathological clearance and surgical resectability in crizotinib-refractory, locally advanced ALK-positive NSCLC. However, these outcomes must be interpreted within the boundaries of a single-case design; validation in prospective clinical trials is necessary to establish standard clinical protocols.
Neoadjuvant Downstaging and Surgical Conversion Mechanics
Copy code to add this image to your page
Ceritinib (LDK378) is a potent, oral, second-generation ATP-competitive inhibitor of ALK tyrosine kinase. By binding the ATP catalytic domain of ALK, it blocks autophosphorylation and suppresses downstream RAS/MAPK, PI3K/AKT, and STAT3 signaling pathways. In crizotinib-resistant ALK-rearranged NSCLC, ceritinib overcomes primary resistance mechanisms, leading to profound metabolic and tumor regression that can convert inoperable stage IIIB disease into a resectable state achieving pathological complete response.
Metabolic Regression and Nodal Downstaging from N3 to N2
Neoadjuvant administration of Ceritinib (LDK378) produced rapid metabolic regression within the primary pulmonary lesion and mediastinal lymphatics. Fluorodeoxyglucose positron emission tomography imaging demonstrated marked attenuation of standardized uptake values. This metabolic response translated directly to anatomical downstaging from stage IIIB(N3) disease to stage IIIA(N2). Consequently, previously unresectable tumor burdens became accessible for complete surgical intervention. Right lower lobe lobectomy with systemic mediastinal lymph node dissection was successfully performed without perioperative complications.
Pathological Complete Response Confirmed Post-Surgical Resection
Histological examination of the resected tissue specimen revealed complete replacement of neoplastic elements by fibrous tissue and inflammatory infiltrate. No residual viable malignant cells were identified across all examined lymph node stations or primary tissue margins; this confirmed a pathological complete response. Downstream ALK phosphorylation ceased following targeted TKI administration. The patient maintained disease-free survival at 12 months post-resection. These findings illustrate the potential for second-generation inhibitors to render crizotinib-resistant tumors operable, although prospective trial cohorts must validate these surgical conversion rates.