LOXO-292 (Selpercatinib) LOXO292 Targeted RET Kinase Inhibition in Solid Tumors
Copy code to add this image to your page
Targeted inhibition of the RET (rearranged during transfection) receptor tyrosine kinase represents a core strategy in managing oncogenic RET-driven malignancies, including RET fusion-positive non-small cell lung cancer (NSCLC) and RET-mutant medullary thyroid carcinoma (MTC). LOXO-292 (Selpercatinib) is a highly selective, ATP-competitive small-molecule inhibitor designed to overcome the structural limitations of early multi-kinase inhibitors (MKIs) such as cabozantinib and vandetanib. Conventional MKIs exhibit potent activity against non-target kinases—specifically VEGFR2 (KDR)—resulting in narrow therapeutic windows, dose-limiting off-target toxicities (e.g., hypertension, proteinuria), and sub-optimal systemic target coverage. In contrast, LOXO292 was synthesized via structure-based drug design to maximize potency against wild-type RET isoforms, oncogenic fusion products (such as KIF5B-RET and CCDC6-RET), and solvent-front or gatekeeper resistance mutations (including RET V804M and V804L), while maintaining exquisite selectivity over non-target kinases within the broader receptor tyrosine kinase family signaling networks.
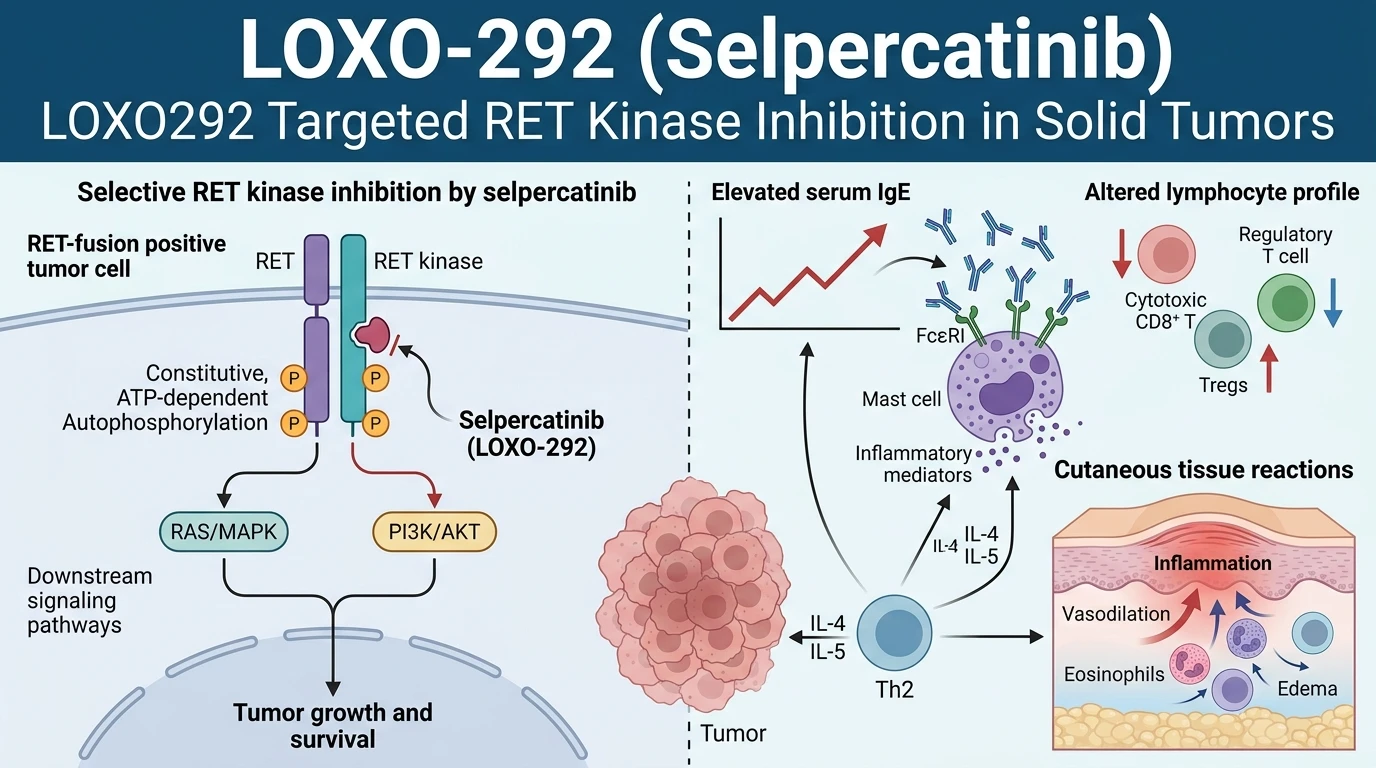
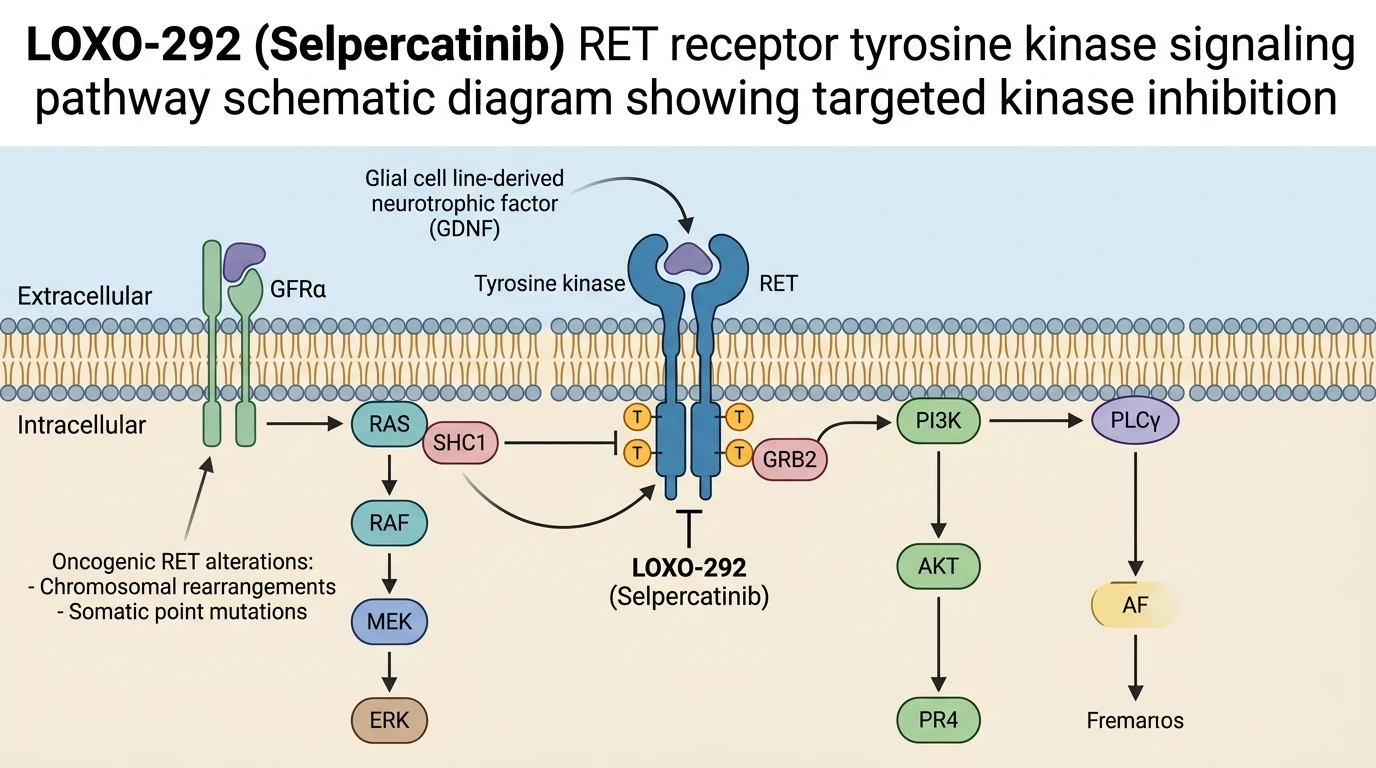
At the molecular level, RET activation relies on ligand binding—such as glial cell line-derived neurotrophic factor (GDNF)—which triggers receptor dimerization and intracellular phosphorylation. In RET-altered malignancies, structural rearrangements or point mutations lead to constitutive activation independent of ligand presence. LOXO-292 (Selpercatinib) specifically targets this activated state by stabilizing an inactive catalytic conformation. Preclinical kinase panels demonstrate that selpercatinib possesses nanomolar potency against RET while displaying over 100-fold selectivity against VEGFR2, FGFR1-3, and EGFR, minimizing off-target cardiovascular and renal side effects.
The biochemical efficacy of selpercatinib stems from its tight-binding kinetics within the active ATP-binding cleft of the RET catalytic domain. By blocking autophosphorylation at key intracellular tyrosine residues (such as Tyr1062), selpercatinib halts downstream signal propagation through the canonical RAS-RAF-MEK-ERK, PI3K-AKT, and PLCγ pathways. This blockade disrupts cellular growth signals, impairs protein synthesis, and initiates apoptosis in RET-dependent tumor cells. Despite its favorable kinome selectivity profile, clinical utilization of LOXO-292 (Selpercatinib) reveals a distinct spectrum of adverse events, particularly affecting mucocutaneous tissue beds.
To characterize the incidence, kinetics, and immunological correlates of mucocutaneous adverse events (MAEs), a comprehensive clinical study analyzed a cohort of 133 patients receiving selpercatinib monotherapy for RET-altered cancers. Over the study period, MAEs exhibited a yearly cumulative incidence of 55%, with 73 patients experiencing a total of 126 discrete events. The median time to event onset was recorded at 57 days post-treatment initiation, reflecting a delayed cutaneous reaction rather than an immediate hypersensitivity phenotype.
Reassuringly, the overwhelming majority of observed MAEs were low-grade in nature; 98% of recorded events were classified as Grade 1 or Grade 2 according to Common Terminology Criteria for Adverse Events (CTCAE). The predominant clinical manifestations were xerostomia (37% of patients), cutaneous rash (18%), periorbital edema (12%), and xerosis (9%). High-grade (Grade 3 or greater) mucocutaneous toxicities were extremely rare, occurring in only 2% of the total event population.
Immunological profiling of patient cohorts yielded key mechanistic insights into MAE pathogenesis. Patients who developed mucocutaneous reactions demonstrated a significantly higher percentage of circulating lymphocytes compared to patients who remained free of MAEs. Additionally, serum IgE levels were significantly elevated in the MAE cohort. These biochemical parameters imply a T-cell and IgE-mediated immune hypersensitivity mechanism rather than direct non-specific epidermal cytotoxicity. The selective activation of immune pathways suggests that RET kinase inhibition in peripheral tissues or non-malignant cutaneous cells may modulate local immune tolerance or barrier function.
From a clinical administration perspective, MAEs presented manageable challenges that did not compromise overall treatment retention. While 14% of patients required temporary dose interruptions or dose reductions to resolve cutaneous symptoms, zero patients (0%) permanently discontinued selpercatinib therapy due to MAEs. Interdisciplinary collaboration between oncologists and dermatologists enabled the implementation of targeted supportive care measures, including topical corticosteroids, oral antihistamines, barrier repair emollients, and sialagogues. These reactive management protocols effectively controlled symptoms, restored quality of life, and permitted continuous target suppression in patients with RET-driven solid tumors.
Pharmacological Characterization and Clinical Cutaneous Safety Profile
Copy code to add this image to your page
LOXO-292 (Selpercatinib) functions as a potent, highly selective ATP-competitive inhibitor of RET receptor tyrosine kinase. By binding the ATP-binding pocket of wild-type RET as well as diverse RET fusion products and gatekeeper resistance mutations (such as V804M/L), it prevents autophosphorylation and blocks downstream activation of RAS-RAF-MEK-ERK and PI3K-AKT cascades. This target inhibition halts cell proliferation and induces apoptosis in RET-dependent tumor phenotypes while sparing non-target kinases.
Incidence and Kinetics of Mucocutaneous Adverse Events
Kinase inhibition profiles dictate both antitumor efficacy and off-target safety. In a clinical cohort of 133 patients, LOXO292 administration induced mucocutaneous adverse events (MAEs) with a yearly cumulative incidence of 55%. These events encompassed 126 discrete occurrences across 73 individuals. Median onset time was 57 days post-treatment initiation. Most dermatologic manifestations were predominantly low-grade in severity; grade 1 and grade 2 events comprised 98% of all reported cases. Primary presentations included xerostomia in 37% of patients, localized rash in 18%, periorbital edema in 12%, and xerosis in 9%. Severe toxicities remained exceedingly rare throughout the observation window.
Lymphocyte Shift and Elevated IgE in Reacting Cohorts
Systemic immune markers revealed distinct biomarker shifts in patients exhibiting dermatologic reactions. Individuals presenting with MAEs demonstrated a significantly higher circulating lymphocyte percentage compared to non-affected cohorts. Furthermore, serum IgE levels were markedly elevated in this subset. These immunological alterations suggest a hyper-reactive hypersensitivity pathway rather than direct cytotoxic necrosis—a mechanistic distinction with management implications. Peripheral eosinophils and inflammatory cytokines may participate downstream in this pathway; however, tissue-level bioptic validation remains incomplete. The correlation between peripheral IgE elevation and dermatologic toxicity warrants further prospective investigation.
Dose Management Preserves Continuity Without Permanent Therapy Cessation
Clinical management strategies mitigated treatment disruptions without compromising target inhibition. Dose modifications proved effective in resolving acute cutaneous reactions. Overall, 14% of patients required temporary dose interruptions or dose reductions. Crucially, zero patients permanently discontinued therapy due to mucocutaneous toxicity. Interdisciplinary dermatological care and targeted topical or oral interventions restored tissue homeostasis; consequently, oncologic control was maintained without treatment cessation. These pharmacodynamic observations highlight the feasibility of sustained RET kinase suppression despite frequent low-grade cutaneous reactivity.